What is Chiropractic Treatment?
Chiropractic care focuses on problems affecting the joints, muscles and nervous system, using treatment, advice and exercise tailored to your individual needs. Find out more →
Read more
Chiropractic treatment has been investigated in clinical trials, systematic reviews and healthcare guidelines around the world, particularly for musculoskeletal conditions such as low back pain and neck pain.
The evidence does not suggest that one treatment is best for every patient. Instead, modern guidelines increasingly support an individualised approach that may combine education, remaining active, exercise and, where appropriate, manual treatments such as mobilisation or spinal manipulation.
On this page, we look at what major UK and international guidelines and systematic reviews actually say about chiropractic treatment — including where the evidence supports its use, where it remains uncertain and what this means for patients.
Want to know more? Request a Callback
Or give us a call, to find out how we can help you with Chiropractic Research: What Does the Evidence Say?.
Book an Appointment
Schedule an appointment for Chiropractic Research: What Does the Evidence Say? tailored to your needs.
There is now a substantial body of research investigating treatments commonly used by chiropractors, particularly spinal manipulation, joint mobilisation, exercise and rehabilitation.
Major healthcare organisations in the UK and internationally include manual therapy or spinal manipulation among the treatment options that may be considered for some musculoskeletal conditions, particularly low back pain.
However, evidence-based chiropractic care does not mean that every patient should receive spinal manipulation. The diagnosis, individual circumstances, patient preferences, exercise, rehabilitation and the natural history of the condition all need to be considered.
The most useful question is therefore not simply “Does chiropractic work?” but “Which treatments are supported for this particular problem, for this particular patient?”
In the UK, the National Institute for Health and Care Excellence (NICE) provides evidence-based recommendations for healthcare professionals.
NICE guideline NG59: Low back pain and sciatica in over 16s covers the assessment and management of low back pain and sciatica in adults. It recommends supporting people with advice and information that encourages them to continue normal activities and considers exercise an important part of management.
NICE also recommends considering manual therapy — including spinal manipulation, mobilisation and soft tissue techniques such as massage — for people with low back pain with or without sciatica.
Importantly, NICE recommends manual therapy only as part of a treatment package that includes exercise, with or without psychological therapy.
This is an important distinction. Current evidence-based care is not simply about repeatedly applying a passive treatment. Hands-on treatment may be one component of a broader approach that also helps the patient restore movement, activity and function.
The World Health Organization guideline for non-surgical management of chronic primary low back pain was published in 2023.
The guideline is international and discipline-neutral. Rather than recommending one profession or treatment, WHO considered education, physical treatments, psychological interventions, medicines and combinations of treatments.
WHO states that spinal manipulative therapy may be offered as part of care for adults, including older adults, with chronic primary low back pain.
This is a conditional recommendation, and WHO rated the certainty of the supporting evidence as very low. This qualification is important when interpreting the recommendation.
WHO also recommends a holistic, person-centred approach and emphasises that people may require a combination of interventions rather than a single treatment used in isolation.
Cochrane systematic reviews bring together and critically evaluate the available evidence from clinical studies.
The updated Cochrane review of spinal manipulative therapy for chronic low back pain included 76 studies involving 11,866 people, with studies published between 1978 and 2024.
The review found that spinal manipulative therapy may provide improvements in pain and function compared with sham manipulation or no treatment. When spinal manipulation was compared with other conservative treatments, the differences were generally smaller.
The authors also identified important limitations in the evidence. Studies differed in their patient populations, techniques, treatment frequency and comparison treatments, and certainty in many of the estimates was low or very low.
The evidence therefore does not show that spinal manipulation is universally superior to other appropriate conservative treatments. It supports considering it as one treatment option within the broader management of chronic low back pain.
Yes. Research into spinal manipulation and manual therapy is not confined to the UK.
Clinical trials, systematic reviews and guidelines have been produced in Europe, North America, Australia and other parts of the world.
For example, the World Health Organization includes spinal manipulative therapy among the physical interventions that may be offered for chronic primary low back pain.
In the United States, clinical guidelines have also included spinal manipulation or mobilisation among non-drug treatment options for some people with low back pain.
Looking across international evidence is useful because it reduces reliance on the recommendations of any one profession, country or healthcare system.
Manipulation and mobilisation have also been extensively investigated for neck pain.
A 2025 systematic review examined international clinical practice guidelines relating to manipulation and mobilisation for neck pain. The review found that high-quality guidelines included recommendations for manipulation or mobilisation, often alongside exercise.
However, neck pain is not one single condition and spinal manipulation is not appropriate for every patient.
Assessment is particularly important before cervical treatment. The clinician should consider the patient’s symptoms, medical history and examination findings and identify circumstances in which treatment should be modified, avoided or referred for further investigation.
For many patients, treatment may therefore combine mobilisation or manipulation with exercise, advice and rehabilitation rather than relying on one technique alone.
The evidence for manual therapy depends considerably on the type of headache being considered.
Cervicogenic headache is associated with structures in the neck. A systematic review and meta-analysis found small short-term improvements in headache intensity, frequency and disability with spinal manipulative therapy, while also concluding that high-quality evidence was lacking and that significant long-term benefits had not been demonstrated.
This should not be interpreted as evidence that every headache is caused by the neck or that every headache should be treated with spinal manipulation.
Migraine, for example, is a neurological disorder. Current research does not establish spinal manipulation as an effective treatment for migraine itself.
Correctly identifying the likely type of headache is therefore important before deciding whether treatment directed at the neck may have a role.
Sciatica usually refers to symptoms associated with irritation or compression of a nerve supplying the leg. It may occur alongside low back pain but is not simply another name for back pain.
NICE includes low back pain with or without sciatica within its recommendation that manual therapy may be considered as part of a treatment package including exercise.
However, treatment needs to be based on the individual presentation and neurological findings.
Progressive weakness, significant neurological loss or symptoms suggesting cauda equina syndrome require urgent medical assessment rather than routine conservative treatment.
One of the clearest themes running through modern musculoskeletal guidelines is that care should not rely solely on passive treatment.
Exercise can be used to improve movement, strength, confidence and physical capacity and to help people return progressively to activities that have become difficult.
This is one reason rehabilitation forms an important part of our approach at Isis Chiropractic Centres.
Where appropriate, hands-on treatment can be combined with exercises selected according to the patient’s condition, capabilities and goals.
The aim is not simply to treat a painful area repeatedly, but to help the patient regain movement, function and confidence as recovery progresses.
Research does not support the idea that spinal manipulation is universally superior to physiotherapy, exercise or every other form of conservative treatment.
Indeed, the differences between appropriate conservative treatments are often relatively modest.
This is one reason modern evidence-based practice is moving away from asking which profession has the single “best” treatment and towards identifying an appropriate combination of interventions for the individual patient.
For one person this may involve more exercise and self-management. Another may benefit from a period of hands-on treatment combined with rehabilitation. Some patients may require investigation or referral rather than chiropractic treatment.
Safety needs to be considered alongside potential benefit for any healthcare intervention.
Temporary soreness, stiffness or an increase in symptoms can occur following spinal manipulation or other forms of manual treatment. Serious adverse events are uncommon, but particular care is required when assessing patients before treatment of the cervical spine.
Clinical assessment should therefore consider the patient’s symptoms, medical history and examination findings and look for indications that manipulation may be inappropriate or that further investigation or referral is required.
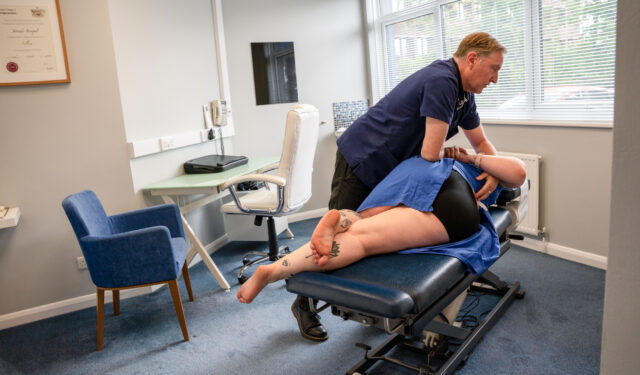
It is also important to recognise that chiropractic care does not necessarily involve high-velocity manipulation. Depending on the patient and diagnosis, treatment may instead include mobilisation, soft tissue techniques, exercise, rehabilitation and advice.
Not every musculoskeletal problem should be treated with chiropractic care, and not every patient who visits a chiropractor should receive spinal manipulation.
Symptoms or examination findings suggesting fracture, infection, cancer, significant neurological compromise or another serious underlying condition may require further investigation or medical referral.
Imaging is also not routinely required for uncomplicated low back pain. NICE recommends against routinely offering imaging in a non-specialist setting and advises considering imaging in specialist settings only when the result is likely to change management.
Recognising when not to treat, when to investigate and when to refer is an important part of evidence-based clinical practice.
Chiropractic has been researched for many decades, and some older studies played an important role in the development of the profession.
These include UK trials comparing chiropractic and hospital outpatient management of low back pain and the Canadian Manga Report, which examined the effectiveness and cost-effectiveness of chiropractic management of low back pain.
These studies are historically interesting, but evidence-based practice should not rely primarily on research from the 1990s when more recent systematic reviews and clinical guidelines are available.
You can read more about one of these influential historical reports on our Manga Report and Chiropractic Research page.
Research provides guidance, but treatment decisions still need to be made for the individual patient.
At Isis Chiropractic Centres, our approach begins by listening to the patient, understanding their symptoms and carrying out an appropriate clinical examination.
We explain what we think may be causing or contributing to the problem and discuss the available options.
Depending on the diagnosis and individual circumstances, care may include joint mobilisation or manipulation, soft tissue techniques, advice, exercise and rehabilitation.
Where treatment is not appropriate, or where further investigation or specialist assessment is indicated, we will explain this and discuss the appropriate next steps.
This approach reflects an important theme running through modern UK and international guidance: musculoskeletal care should be individualised, encourage appropriate activity and self-management, and combine treatments where this is supported by the patient’s needs and the available evidence.
There is credible research supporting the use of spinal manipulation and other forms of manual therapy for some musculoskeletal conditions, particularly low back pain.
International guidelines recognise these treatments as possible components of care, but they do not suggest that spinal manipulation is appropriate for everyone or that it should replace exercise, self-management or other evidence-based treatments.
The evidence is also stronger for some conditions than others. Low back pain has a substantial research base; there is supportive evidence for some approaches to neck pain and cervicogenic headache, while evidence for other conditions may be limited or uncertain.
For us, evidence-based chiropractic care therefore means combining the best available research with careful clinical assessment, patient preferences and an individual treatment and rehabilitation plan.
The references below include clinical guidelines and systematic reviews from UK and international sources. Links are provided so that readers can examine the original evidence and recommendations.
Chiropractic care focuses on problems affecting the joints, muscles and nervous system, using treatment, advice and exercise tailored to your individual needs. Find out more →
Chiropractic treatment is tailored to your individual needs and may include joint mobilisation or manipulation, soft tissue techniques, advice and exercise.
Back pain can have many causes. Learn how we assess back pain and use individualised treatment and rehabilitation to help improve movement and function.
The 1993 Manga Report examined the effectiveness and cost-effectiveness of chiropractic care for low back pain. Learn what the report concluded and how it fits into modern chiropractic research.